


Copyright Notice
Attribution Statement: LactMed is a registered trademark of the U.S. Department of Health and Human Services.
Bookshelf ID: NBK501002PMID: 30000061

An official website of the United States government

NCBI Bookshelf. A service of the National Library of Medicine, National Institutes of Health.
Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development; 2006-.
CASRN: 100986-85-4
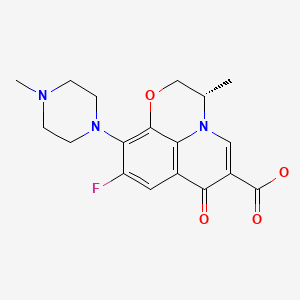
Levofloxacin amounts in breastmilk appear to be considerably lower than the infant dose and would not be expected to cause any serious adverse effects in breastfed infants. Fluoroquinolones such as levofloxacin have traditionally not been used in infants because of concern about adverse effects on the infants' developing joints. However, more recent studies indicate little risk.[1,2] The calcium in milk might prevent absorption of the small amounts of fluoroquinolones in milk,[3] but insufficient data exist to prove or disprove this assertion. Use of levofloxacin is acceptable in nursing mothers with monitoring of the infant for possible effects on the gastrointestinal flora, such as diarrhea or candidiasis (thrush, diaper rash). Avoiding breastfeeding for 1 hour or more after an intravenous dose and 4 to 6 hours after an oral dose should decrease the exposure of the infant to levofloxacin in breastmilk. Maternal use of eye drops that contain levofloxacin presents negligible risk for the nursing infant.
Maternal Levels. One woman was given levofloxacin 500 mg daily intravenously for 9 days, then orally for 17 days. Twenty-six breastmilk samples were obtained, beginning on day 10 of therapy and continued for 6 days after the discontinuation of therapy. A pharmacokinetic model that was developed predicted that a peak milk level of 8.2 mg/L would occur 5 hours after the dose. The milk levels fell with an estimated half-life of 7 hours. Traces of levofloxacin were still detectable in breastmilk 65 hours after the dose. The authors calculated that an exclusively breastfed infant whose mother was taking 500 mg daily would receive 1.25 mg daily in breastmilk, which is far below the dose of levofloxacin used in children.[4]
Two nursing mothers each took one 500 mg capsule of levofloxacin (Tavanic-Sanofi, Istanbul) orally. Eleven complete collections of breastmilk were taken over the following 24 hours. Peak levofloxacin milk levels of 265 and 258 mcg/L occurred at 2.5 and 3 hours, respectively, in the two mothers. Average milk levels were 101 and 105, mcg/L, respectively. The half-lives in milk were 4.95 and 5.33 hours, respectively.[5] Using the average milk levels, a fully breastfed infant would receive an average of 15.5 mcg/kg daily.
Five women with atypical pneumonia were receiving intravenous levofloxacin 400 mg once daily. Milk samples were collected at 0.5, 1, 2, 4, 6, 8, 10, 12, and 24 hours after the last dose of the drug. The peak milk level averaged 14.6 mg/L and occurred at 0.5 hours after the dose. The half-life in milk averaged 4.57 hours. The daily infant dosage was 0.4 mcg/kg for exclusively breastfed infants, which is less than 10% of the recommended therapeutic dose for 0 to 12-month-old infants (10 mg/kg once daily). This translated into an average relative infant dose of 6.1%. The authors recommended waiting for 1 hour or longer after a dose to resume breastfeeding after a dose to reduce the infant exposure. Five other women who collected milk samples unsupervised at unclear times had a calculated average RID of 8.2%.[6]
Using the pooled results from two clinical trials, 98 breastmilk samples were collected from 20 women pre-dose, and at 2, 4, 6 and 8 hours after the dose at 5 to 12 weeks postpartum and after 4 or more weeks of levofloxacin therapy initiated during pregnancy for rifampicin-resistant tuberculosis . Some opportunistic samples were also obtained 6 to 12 months postpartum. A population pharmacokinetic model was built using NONMEM. The model showed rapid equilibration between maternal plasma and milk, with a half-life of 7.5 minutes. The median peak milk concentration was 16.9 mg/L. The estimated daily amount of levofloxacin excreted into breastmilk ranged from 3.82 to 10.8 mg, which resulted in an RID of about 6%.[7]
Infant Levels. Thirteen breastfed (6 exclusive, 7 mixed) infants with a median age of 6.97 weeks had serum samples (15 total) taken while their mothers were receiving levofloxacin 750 or 1000 mg daily. Eighty percent of the concentrations were above the level of quantification, with most below 1 mg/L. The highest was about 4 mg/L and another was about 2.5 mg/L.[8]
Relevant published information was not found as of the revision date.
Relevant published information was not found as of the revision date.
(Systemic) Ciprofloxacin; (Ophthalmic) Ciprofloxacin, Ofloxacin
Levofloxacin
100986-85-4
Breast Feeding
Milk, Human
Anti-Infective Agents
Antibacterial Agents
Quinolones
Fluoroquinolones
Disclaimer: Information presented in this database is not meant as a substitute for professional judgment. You should consult your healthcare provider for breastfeeding advice related to your particular situation. The U.S. government does not warrant or assume any liability or responsibility for the accuracy or completeness of the information on this Site.
Attribution Statement: LactMed is a registered trademark of the U.S. Department of Health and Human Services.
Your browsing activity is empty.
Activity recording is turned off.
See more...