


NCBI Bookshelf. A service of the National Library of Medicine, National Institutes of Health.
Feingold KR, Adler RA, Ahmed SF, et al., editors. Endotext [Internet]. South Dartmouth (MA): MDText.com, Inc.; 2000-.

ABSTRACT
This chapter presents the highlights of the 2026 ACC/AHA guideline on the management of dyslipidemia and the 2019 ESC/EAS guidelines for the management of dyslipidemias and the 2025 focused update. The key principles for evaluating, deciding on treatment goals, and treating patients with dyslipidemia are addressed. This should provide the reader with the ability to manage patients with dyslipidemia. For complete coverage of all related areas of Endocrinology, please visit our on-line FREE web-text, WWW.ENDOTEXT.ORG.
INTRODUCTION
Atherosclerotic cardiovascular disease (ASCVD) remains the foremost cause of death among chronic diseases. An aging population combined with an atherogenic lifestyle increases the risk of ASCVD. Even so, mortality from ASCVD has been declining in most developed countries. This decline comes from improvements in preventive measures and better clinical interventions. One of the most important advances in the cardiovascular field resulted from identifying risk factors for ASCVD. Risk factors directly or indirectly promote atherosclerosis, or they otherwise predispose to vascular events. The major risk factors are cigarette smoking, dyslipidemia, hypertension, hyperglycemia, inflammation, chronic renal disease, and advancing age. Dyslipidemia consists of elevations of atherogenic lipoproteins (LDL, VLDL, Lp(a), and remnants) and low levels of HDL. Advancing age counts as a risk factor because it reflects the impact of all risk factors over the lifespan. Several other factors, called risk enhancing factors are associated with a higher risk for ASCVD. Lifestyle factors (for example, diet and physical inactivity) contribute importantly to both major and enhancing risk factors. Hereditary factors undoubtedly contribute to the identifiable risk factors; but genetic influences also affect ASCVD risk through other ways not yet fully understood (1).
In this chapter I will discuss the 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/ APhA/ASPC/NLA/PCNA Guideline on the management of dyslipidemia (2,3) and the 2019 ESC/EAS Guidelines for the management of dyslipidemias and the 2025 focused update (4,5). Additionally, I will discuss the key principles in the management of dyslipidemia. For a discussion of guidelines for dyslipidemia in children and adolescents see the Endotext chapter entitled “Guidelines for Screening, Prevention, Diagnosis and Treatment of Dyslipidemia in Children and Adolescents” (6) and for a discussion of dyslipidemia during pregnancy see the Endotext chapter entitled “Effect of Pregnancy on Lipid Metabolism and Lipoprotein Levels” (7).
2026 ACC/AHA GUIDELINE ON THE MANAGEMENT OF DYSLIPIDEMIA
Top Take Home Messages
- 1.
Treat dyslipidemia earlier to reduce lifelong risk of prolonged exposure to atherogenic lipoproteins. This is particularly important in individuals with Familial Hypercholesterolemia (FH), LDL-C levels > 160mg/dL, and a family history of premature ASCVD.
- 2.
To calculate the 10- and 30-year risk assessment to guide lipid-lowering therapy (LLT) in primary prevention in adults aged 30 to 79 years use the PREVENT equations (https:
//professional .heart.org/en/guidelines-and-statements /prevent-calculator). To refine the estimated risk, consider risk enhances not included in the PREVENT-ASCVD equations and in select individuals consider the use of coronary artery calcium (CAC) score. - 3.
Therapy to lower LDL-C can be considered in adults for primary prevention of ASCVD with a 10-year PREVENT-ASCVD risk estimate of 3% to <5% (borderline risk) and should be considered for those at 5% to <10% (intermediate risk) 10-year risk after a clinician–patient discussion.
- 4.
Both LDL-C and non–HDL-C treatment goals and percentage reduction in LDL-C are back to guide LLT.
- 5.
Apolipoprotein B (Apo B) can be useful to improve risk assessment and guide therapy once LDL-C and non–HDL-C goals are met, particularly in those with elevated triglycerides (TG) (>200 mg/dL), diabetes, or low LDL-C levels (<70 mg/dL).
- 6.
Lipoprotein(a) [Lp(a)] should be measured at least once to identify individuals at increased risk of ASCVD. Levels >125 nmol/L (>50 mg/dL) are associated with an approximately 1.4-fold increased ASCVD risk and values >250 nmol/L (>100 mg/dL) are associated with >2-fold higher risk. An elevated Lp(a) is an indication for more intensified LDL-C lowering and management of other risk factors.
- 7.
CAC scoring in men >40 years of age and women >45 years of age can improve risk assessment and guide LDL-C and non–HDL-C goals. Both the absolute amount of CAC and the corresponding standardized percentile (currently based on age, sex, and race) have prognostic importance and help to reclassify risk in adults.
- 8.
Decreasing LDL-C is recommended for primary prevention in adults aged 40 to 75 years with diabetes, chronic kidney disease stage 3 or 4, or human immunodeficiency virus, regardless of the LDL-C level. After age 75 years, LDL-C–lowering pharmacotherapy can be considered in conjunction with lifestyle interventions to reduce ASCVD risk.
- 9.
In secondary prevention, the LDL-C goal is <55 mg/dL (1.4 mmol/L) and the non–HDL-C goal is <85 mg/dL (2.2 mmol/L) in patients at very high risk of ASCVD events. Only a small number of patients with ASCVD are not at very high risk and those patients have an LDL-C goal of <70 mg/dL and non-HDL-C <100mg/dL.
- 10.
In patients with persistently elevated TG, statin therapy remains the foundation of pharmacotherapy as an adjunct to lifestyle intervention to reduce ASCVD risk. Treatment for prevention of pancreatitis, particularly in individuals with TG levels >1000 mg/dL (11.3 mmol/L), may also include TG-lowering therapies.
Screening Recommendations
Because abnormal lipid levels are common in adults and children (age 18 years and younger), affecting 20% to 25% of the population the guidelines recommend screening patients for dyslipidemia. Approximately 25% of adults have an LDL-C >130 mg/dL (3.4 mmol/L) and severe lipid abnormalities such as the heterozygous FH phenotype affect 1 in 250 to 300 individuals. The guidelines recommend.
- In adults screening with a lipid panel is recommended at age 19 and at least every 5 years thereafter. In individuals with other ASCVD risk factors more frequent screening is recommended.
- In children 9-11 years of age screening is recommended for the early diagnosis of FH and other lipid disorders.
- In individuals with a first or second degree relative with FH, severe hypercholesterolemia, or premature ASCVD it is reasonable to screen at age 2 (cascade screening).
A standard fasting or non-fasting lipid panel (Total cholesterol, LDL-C, TG, HDL-C, Non-HDL-C) is recommended. Non-HDL-C is calculated as total cholesterol minus HDL-C. A fasting lipid panel should be obtained in patients with elevated TG (>400mg/dL) with a non-fasting lipid panel, patients known to have or suspected of having elevated TG levels, patients with a family history of dyslipidemia, or patients with premature ASCVD or family history of ASCVD. LDL-C levels should be calculated using the Martin/Hopkins or Sampson/NIH equations. The Martin/Hopkins or Sampson/NIH equations are preferred over LDL-C calculated by the Friedewald equation or by direct LDL-C measurements (other than beta-quantitation). Routine use of advanced lipoprotein testing, such as gradient gel electrophoresis, density gradient ultracentrifugation, NMR spectroscopy, and ion mobility analysis, is not recommended. Advanced lipoprotein testing should be limited to scenarios where the availability of such information is likely to change the treatment plan. Measurement of Apo B can be useful to improve risk assessment and guide therapy once LDL-C and non–HDL-C goals are met, particularly in those with elevated TG (>200 mg/dL), diabetes, or low LDL-C levels (<70 mg/dL). The measurement of Lp(a) is recommended at least once in all adults. In individuals with elevated Lp(a) levels, FH, premature ASCVD, or premature aortic stenosis cascade screening of first-degree relatives is recommended as Lp(a) levels are primarily genetically determined. It is preferable to measure Lp(a) using assays that are calibrated in molar units (i.e., nmol/L) and that are apo(a) isoform–insensitive.
After initiating lipid lowering therapy (LLT), adjusting the dose, or changing therapy a lipid panel should be obtained after 4-12 weeks. Once on a stable LLT regimen a lipid panel can be checked every 6-12 months.
Lifestyle
The guidelines recommend the following.
- In children and healthy adults, healthy dietary patterns, regular physical activity, maintenance of a healthy weight, healthy sleep, stress management, and avoidance of tobacco products should be promoted and reinforced lifelong to reduce the risk for dyslipidemia and ASCVD.
- In adults and children with or without ASCVD, a diet emphasizing intake of fruits, vegetables, nuts, legumes, whole grains, and fiber, while replacing saturated and trans fats with dietary monounsaturated and polyunsaturated fats, is recommended to decrease LDL-C levels and reduce ASCVD risk.
- In individuals who are overweight or obese weight reduction and maintenance of a healthy weight are recommended to improve dyslipidemia.
- In individuals with dyslipidemia, regular physical activity that includes moderate-to-vigorous intensity aerobic exercise for >150minutes/week along with upper and lower body resistance exercise 2 days/week should be recommended.
In patients with hypertriglyceridemia the guidelines recommend.
- In adults with fasting TG levels of 150 to 499 mg/dL, a diet that is low in added sugar (<6% of total calories), refined carbohydrates, and saturated fat, and that minimizes alcohol is beneficial to reduce TG and ASCVD risk.
- In adults with fasting TG levels of 500 to 999 mg/dL, a diet that is low in added sugar (<5% of total calories), refined carbohydrates, and saturated fat, with no alcohol and individualized limitation of total fat (typically 20-25% of total calories) is beneficial to reduce TG for the reduction of ASCVD risk and risk of pancreatitis.
- In adults with fasting TG levels >1000 mg/dL, a diet that is very low in total fat (10-15% of total calories) and refined carbohydrates, with elimination of alcohol and added sugars is beneficial to reduce TG and risk for pancreatitis.
- In adults with fasting TG levels >150 mg/dL or non-fasting TG levels >175 mg/dL, improvement in life-style factors related to overweight/obesity and cardio-kidney-metabolic syndrome include weight loss of 5% to 10%, moderate-to-vigorous intensity physical activity of >150 minutes/week, and upper and lower body resistance exercise 2 days/week to reduce TG levels.
Primary Prevention
The first step is to determine 10-year risk using the PREVENT calculator (https://professional.heart.org/en/guidelines-and-statements/prevent-calculator). The PREVENT calculator includes age, sex, blood pressure, total cholesterol and HDL-C, diabetes status, tobacco use, kidney function (eGFR), statin use, and antihypertensive medication use with optional additional variables if available (HbA1c, urinary albumin/creatinine ratio, and zip code to represent social deprivation index and acknowledge social determinants of cardiovascular risk). Risk estimates from PREVENT-ASCVD equations tend to be 40% to 50% lower than 10-year risk estimates from the previously recommended pooled cohort equations.
Individuals are categorized based on their 10-year ASCVD risk estimate into low-risk (<3%), borderline-risk (3% to <5%), intermediate-risk (5% to <10%), or high-risk (>10%) groups. Additionally, the PREVENT calculator provides the 30-year risk of ASCVD, which can be helpful in younger individuals in guiding decisions. Risk enhancers (table 1) and the CAC score can be used to further define risk. For example, in adults with a borderline 10-year ASCVD risk estimate (3% to <5%) if hsCRP is measured and is >2 mg/L on 2 successive occasions with no identifiable cause high-intensity statin therapy can be useful to reduce the risk of ASCVD based on the JUPITER study. In adults at intermediate risk (5% to <10%) or select adults at borderline (3% to <5%) risk, if the CAC score is 0 Agatston units (AU), and there is a preference to avoid LLT it is reasonable to defer therapy and reassess with repeat CAC testing in 3 to 7 years. In adults at intermediate risk and select adults at borderline risk, if the CAC score is >0 AU, it is recommended to initiate LLT, particularly if the CAC score is >100 AU or >75th standardized percentile to reduce ASCVD risk. Individuals with a CAC >100 have a 10-year ASCVD event rate comparable to high-risk adults while individuals with a CAC >300 are comparable to adults with established, treated ASCVD. Once LLT is initiated, repeat CAC testing is not indicated because statin therapy often increases CAC scores, even though they may stabilize or reduce plaque volume by decreasing cholesterol and inflammation while improving clinical outcomes. In adults with no prior ASCVD who are likely to have a high burden of noncalcified plaque (e.g., inflammatory disorders, persons living with HIV, and diabetes), selective use of coronary computed tomography angiography (CCTA) may be useful to inform risk assessment and guide decisions regarding treatment intensity of LLT.
Table 1.
Risk Enhancers
| History of premature ASCVD in a parent or sibling (onset age <55 y for men, <65 y for women) |
| Higher risk ancestry (e.g., South Asian, Filipino) |
| High polygenic risk if measured |
| Chronic inflammatory diseases (e.g., systemic lupus, rheumatoid arthritis, advanced psoriasis, inflammatory arthritis, etc.) |
| Lp(a) >125 nmol/L or >50 mg/dL |
| hsCRP >2 mg/L on >1 occasion if measured |
| TG persistently >175 mg/dL if non-fasting and >150 mg/dL if fasting |
| CKM syndrome |
| LDL-C persistently 160–189 mg/dL, non–HDL-C 190–219 mg/dL, or apoB >120 mg/dL |
| Reproductive risk markers- premature menopause, preeclampsia, gestational diabetes, gestational hypertension, preterm delivery, polycystic ovarian syndrome |
CKM= cardiovascular-kidney-metabolic. The common characteristics of the CKM syndrome include abdominal obesity (high BMI and/or large waist circumference), insulin-resistant glucose metabolism (hyperinsulinemia, impaired fasting glucose, impaired glucose tolerance, type 2 diabetes), dyslipidemia (high TG and low HDL-C concentrations), increased blood pressure, and sometimes microalbuminuria, proteinuria, or chronic kidney disease (CKD).
The next step after risk determination is to decide on whether to use LLT. Table 2 provides guidance on deciding whether to treat and how aggressively to treat. Clinicians and their patients should engage in a discussion of the patient’s ASCVD risk, expected risk reduction benefits from LLT, possible harm, costs, and patient preferences to make individualized treatment decisions and/or consider additional options for evaluation to aid in decision-making.
Table 2.
Recommendations for Primary Prevention in Patients 30 to 79 Years With LDL-C Levels 70 to 189 mg/dL
| Low 10-year Risk (<3%) for ASCVD |
| In adults who have an LDL-C <160 mg/dL and a 30-year risk estimate of <10%, counseling on health behaviors is recommended |
| In adults aged 30 to 59 years, but with an LDL-C of 160 to189 mg/dL or a 30-year ASCVD risk >10%, a moderate-intensity statin is reasonable to reduce cumulative exposure to atherogenic lipoproteins |
| Borderline (3% to <5%) and Intermediate (5% to <10%) 10-year Risk for ASCVD |
| In adults at borderline (3% to <5%) 10-year risk for ASCVD in whom a decision is made to initiate statin therapy a moderate-intensity statin is reasonable to achieve a 30% to 49% LDL-C reduction to reduce ASCVD risk |
| In adults at intermediate (5% to <10%)10-year risk for ASCVD, at least a moderate-intensity statin is recommended to achieve a 30% to 49% LDL-C reduction and to reduce ASCVD risk; for those in the higher end of this risk range, a high-intensity statin is beneficial to further reduce LDL-C by >50% and reduce ASCVD risk |
| In adults at borderline (3% to <5%) or intermediate (5% to <10%) 10-year risk for ASCVD in whom statin therapy is initiated, it is reasonable to treat to a goal LDL-C <100 mg/dL and non–HDL-C <130 mg/dL to reduce ASCVD risk |
| High 10-year Risk (>10%) for ASCVD Risk |
| High-intensity statin therapy is recommended to achieve an LDL-C reduction of >50% and is reasonable to treat to a goal LDL-C <70 mg/dL and non–HDL-C <100 mg/dL |
| In adults on maximally tolerated statin therapy it is reasonable to add ezetimibe if a goal LDL-C <70 mg/dL and non–HDL-C <100 mg/dL is not achieved |
| In adults on maximally tolerated statin with or without ezetimibe, it may be reasonable to add a PCSK9 mAb or bempedoic acid if a goal of LDL-C<70 mg/dL and non–HDL-C <100 mg/dL is not achieved |
| Special Considerations in Primary Prevention |
| In individuals with a life expectancy of <1 year, it may be reasonable to discontinue drug therapy to avoid unnecessary medication use or adverse medication effects |
| In adults with a baseline untreated LDL-C <70 mg/dL and non–HDL-C <100 mg/dL and without additional ASCVD risk factors, initiation of drug therapy for primary prevention is unlikely to reduce ASCVD risk. |
Figure 1 provides an overview of the approach in individuals without ASCVD including CAC scans.

Figure 1.
Primary prevention in adults without ASCVD.
As statins are the LLT of choice to lower LDL-C levels the effectiveness of the different statins is shown in table 3.
Table 3.
Categories of Intensities of Statins
| Drug | Low-Intensity 20-25% ↓ LDL-C | Moderate-Intensity 30-49%↓ LDL-C | High Intensity >50%↓ LDL-C |
|---|---|---|---|
| Lovastatin | 10-20 mg | 40-80 mg | |
| Pravastatin | 10-20 mg | 40-80 mg | |
| Simvastatin | 10 mg | 20-40 mg | |
| Fluvastatin | 20-40 mg | 80 mg | |
| Pitavastatin | 1-4 mg | ||
| Atorvastatin | 5 mg | 10-20 mg | 40-80 mg |
| Rosuvastatin | 5-10 mg | 20-40 mg |
Severe Hypercholesterolemia (LDL-C >190 mg/dL)
Patients with heterozygous FH have a high risk of ASCVD. Because of this the standard risk assessment tools developed for the general population should not be used to calculate 10- or 30-year ASCVD risk in these individuals. Additionally, a CAC of 0 should not be used to “de-risk” patients with FH or justify deferral of statin therapy. Cascade screening of relatives is indicated.
With regards to genetic testing the guidelines recommend:
- In adults with possible, probable, or definite FH genetic testing is beneficial to identify individuals at highest risk of cardiovascular events and to facilitate cascade screening.
- In adults with severe hypercholesterolemia with an LDL-C >190 mg/dL without a secondary cause, genetic testing for FH can be useful to identify those with FH who are at higher risk of ASCVD events.
- In adults with an LDL-C between 160 to 189 mg/dL without an identified secondary cause, genetic testing for FH may be considered to identify those with FH who are at higher risk of events.
Individuals with a genetic identified cause of FH have an increased risk of ASCVD compared to individuals with similar LDL-C levels. A significant number of patients with documented genetic variants causing FH have LDL-C levels < 190mg/dL.
Recommendations for the management of patients with LDL-C >190mg/dL are shown in table 4 and figure 2. Recommendations for the management of patients with homozygous FH are shown in table 5.
Table 4.
Recommendations for the Management of Patients with an LDL-C Greater than 190mg/dL
| Secondary causes should be excluded and addressed to reduce LDL-C |
| Treatment with maximally tolerated statin therapy is recommended to lower LDL-C |
| In patients with severe hypercholesterolemia with an LDL-C >190 mg/dL and without clinical ASCVD, additional ASCVD risk factors, HeFH, or subclinical atherosclerosis the recommended goal is an LDL-C <100 mg/dL and a non–HDL-C goal of <130 |
| In patients with severe hypercholesterolemia and clinical or genetic confirmation of HeFH, additional ASCVD risk factors, or documented coronary calcification the recommended goal is an LDL< 70mg/dL and non-HDL-C < 100mg/dL |
| In patients with severe hypercholesterolemia with an LDL-C >190 mg/dL and clinical ASCVD the recommended goal is an LDL < 55mg/dL and non-HDL-C < 85mg/dL |
| If necessary one can add ezetimibe, a PCSK9 mAb, inclisiran, and/or bempedoic acid to reach the goals described above. |

Figure 2.
The evaluation and management of severe hypercholesterolemia (LDL-C> 190mg/dL).
Table 5.
Management of Patients with Homozygous Familial Hypercholesterolemia
| Consultation with a lipid specialist is recommended for consideration of advanced LDL-C–lowering drug therapies and/or lipoprotein apheresis to lower LDL-C |
| Treatment with maximally tolerated statin therapy is recommended to reduce ASCVD risk |
| The addition of ezetimibe, PCSK9 mAb, and/or bempedoic acid is reasonable to lower LDL-C in patients on maximally tolerated statin therapy |
| In patients on maximally tolerated statin therapy, ezetimibe, and PCSK9 mAb with an LDL-C ≥100 mg/dL the addition of evinacumab may be reasonable to lower LDL-C |
| In patients on maximally tolerated statin therapy, ezetimibe, and PCSK9 mAb with LDL-C ≥100 mg/dL the addition of lomitapide with regular monitoring for hepatic safety may be reasonable to lower LDL-C. |
Diabetes in Adults Without Established ASCVD
Calculate ASCVD 10-year risk using the PREVENT calculator. The treatment recommendations for patients with diabetes are shown in table 6 and figure 3. Diabetes specific risk enhances are shown in table 7.
Table 6.
Recommendations for Adults with Diabetes Without Established ASCVD
| In adults 40 to 75 years of age without clinical ASCVD, moderate-intensity statin therapy is indicated to achieve a >30% to 49% reduction in LDL-C and an LDL-C <100 mg/dL and non–HDL-C <130 mg/dL |
| In adults who have statin-attributed side effects, initiation of ezetimibe and/or bempedoic acid or a PCSK9 mAb is recommended to lower LDL-C |
| In adults 40 to 75 years of age who have multiple ASCVD risk factors, it is reasonable to prescribe high-intensity statin therapy to achieve a >50% reduction in LDL-C and an LDL-C <70 mg/dL and non–HDL-C <100 mg/dL |
| In adults without ASCVD but with additional ASCVD risk factor(s) on a statin with an LDL-C <100 mg/dL and elevated fasting TG (150–499 mg/dL, the addition of icosapentethyl may be considered |
| In adults with a 10-year ASCVD risk of >10% by the PREVENT-ASCVD equations, it may be reasonable to add ezetimibe or a PCSK9 mAb to maximally tolerated statin therapy to achieve an LDL-C goal of <70 mg/dL and non–HDL-C <100 mg/dL |
| In adults >75 years of age and an estimated life expectancy of at least 2.5 years, it may be reasonable to initiate moderate-intensity statin therapy after a clinician–patient discussion of potential benefits and risks |
| In adults 20 to 39 years of age with diabetes of long duration (≥10 years of type 2 diabetes, ≥20 years of type 1 diabetes), albuminuria (>30 μg of albumin/mg creatinine), eGFR <60, retinopathy, neuropathy, or ankle-brachial index <0.9, it may be reasonable to initiate moderate-intensity statin therapy |
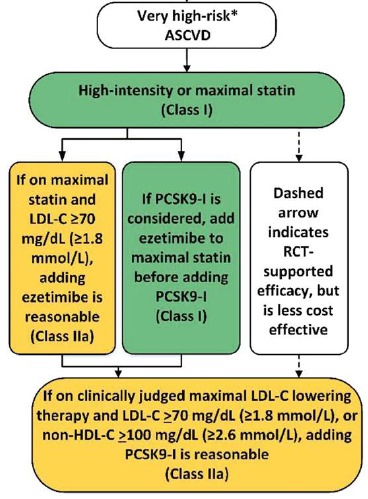
Figure 3.
Management of Patients with Diabetes without ASCVD.
Table 7.
Diabetes-Specific Risk Enhancers
| Long duration (>10 y for type 2 diabetes or >20 y for type 1 diabetes) |
| Albuminuria >30 μg of albumin/mg creatinine |
| eGFR <60 mL/min/1.73 m2 |
| Retinopathy or Neuropathy |
| Ankle-brachial index <0.9 |
Patients with ASCVD
Guidelines for patients with ASCVD are shown in table 8 and figure 4 and 5. The majority of patients with clinical ASCVD are likely to be at very high risk. Very high risk is defined as a history of two or more major ASCVD events (ACS within past 12 months, history of MI [other than ACS above], history of ischemic stroke, symptomatic PAD) or one major ASCVD event and two or more high-risk conditions (age >65 years of age, coronary artery revascularization, current smoker, diabetes, chronic kidney disease, history of heart failure, hypertension, LDL-C >100 mg/dL despite maximally tolerated statin + ezetimibe).
Table 8.
Management in Patients with Clinical ASCVD
| Clinical ASCVD Not at Very High Risk |
| In adults with clinical ASCVD who are not at very high risk, high-intensity statin therapy should be initiated to achieve a >50% reduction in LDL-C and a goal LDL-C <70 mg/dL and non–HDL-C <100 mg/dL |
| In adults with clinical ASCVD who are not at very high risk and on maximally tolerated statin therapy, it is reasonable to add ezetimibe, a PCSK9 mAb, or bempedoic acid (selection depending on degree of LDL-C lowering needed and patient preference) to achieve a goal LDL-C <70 mg/dL and non–HDL-C <100 mg/dL or even lower goal LDL-C <55 mg/dL and non–HDL-C <85 mg/dL |
| Clinical ASCVD at Very High Risk |
| In adults with clinical ASCVD who are at very high risk, high-intensity statin therapy should be initiated to achieve a >50% reduction in LDL-C and a goal LDL-C <55 mg/dL and non–HDL-C <85 mg/dL |
| In adults with clinical ASCVD who are at very high risk and on maximally tolerated statin therapy, ezetimibe, bempedoic acid, and/or a PCSK9 mAb should be added (selected based on the degree of LDL-C lowering needed and patient preference) to achieve a goal LDL-C <55 mg/dL and non–HDL-C <85 mg/dL |
| In adults with clinical ASCVD who are at very high risk and on maximally tolerated statin therapy with or without ezetimibe, it is reasonable to add inclisiran in those unable to tolerate or obtain evolocumab or alirocumab or have a strong preference for less frequent dosing to achieve an LDL-C goal <55 mg/dL and non–HDL-C <85 mg/dL |
| Heart Failure With Reduced Ejection Fraction (HFrEF) |
| In adults with HFrEF attributable to ischemic heart disease who have a reasonable life expectancy (3-5 years) and are not already on a statin and have ASCVD, it may be reasonable to consider initiation of moderate-intensity statin therapy to reduce the occurrence of ASCVD events |
| In adults with HFrEF who do not have clinical ASCVD or another indication for LLT, initiation of LLT is not recommended to reduce clinical events or mortality. |

Figure 4.
ASCVD prevention in not very high-risk patients with ASCVD.

Figure 5.
ASCVD prevention in very high-risk patients with ASCVD.
Management of Adults with Subclinical Coronary Atherosclerosis Detected by CAC Score (Men >40 or Women >45 Years)
Recommendations for patients with subclinical atherosclerosis detected by CAC are described in table 9 and figure 6. These recommendations are for patients with subclinical ASCVD who have not had clinical events.
Table 9.
Recommendations for Management of Adults With Subclinical Coronary Atherosclerosis (Men >40 or Women >45 Years)
| In adults with a CAC score of >1000 AU, treatment with LLT is recommended to achieve a >50% reduction in LDL-C and a goal LDL-C <55 mg/dL and non–HDL-C <85 mg/dL |
| In adults with a CAC score of >100 to 999 AU or >75th standardized percentile, treatment with LLT is recommended to achieve a >50% lowering in LDL-C and a goal LDL-C <70 mg/dL and non–HDL-C <100 mg/dL |
| In adults with a CAC score of 1 to 99 AU and <75th standardized percentile, or with an incidental finding of mild CAC on noncardiac CT scan, treatment with moderate-intensity statin therapy is reasonable to achieve a >30% to 49% reduction in LDL-C and a goal LDL-C <100 mg/dL and non–HDL-C <130 mg/dL |
| In adults with a CAC score of >300 to 999 AU, it is reasonable to intensify therapy by increasing the intensity of statin therapy or, if needed, adding ezetimibe, a PCSK9 mAb, or bempedoic acid to achieve a goal LDL-C <55 mg/dL and non–HDL-C <85 mg/dL |
| In adults with no prior ASCVD who have moderate-to-severe incidental coronary atherosclerosis identified on noncardiac CT scans, it is reasonable to initiate high-intensity statin therapy to achieve at least a >50% reduction in LDL-C and a goal LDL-C <70 mg/dL and non–HDL-C <100 mg/dL |
| In adults with no prior ASCVD who have mild incidental CAC, moderate-intensity statin therapy is reasonable to achieve a >30% to 49% reduction in LDL-C and a goal LDL-C <100 mg/dL and non–HDL-C goal <130 mg/dL |
| For those individuals who are not on LLT and already have a baseline LDL-C below the recommended targets for CAC levels, treatment with LLT is still recommended with the caveat to achieve at least a >30% reduction in baseline LDL-C level |

Figure 6.
Recommendations for patients with subclinical atherosclerosis detected by CAC score.
Recommendations for Patients over Age 75
The recommendations for individuals over age 75 are shown in table 10.
Table 10.
Recommendations for Individuals Over Age 75
| In older adults, the benefit-risk discussion should include patient priorities, functional status, multimorbidity, frailty, polypharmacy, and life expectancy, and should not be based solely on chronological age when considering the decision to discontinue LLT |
| In adults >75 years of age with an estimated life expectancy of at least 2.5 years, it may be reasonable to initiate moderate-intensity statin therapy after a clinician–patient discussion of potential benefits and risks to reduce ASCVD risk |
| In patients with a life expectancy of <1 year, it may be reasonable to discontinue LDL-lowering therapy to avoid unnecessary medication use or adverse medication effects |
| In adults aged >75 years with an estimated life expectancy of at least 2.5 years, and for whom the decision regarding LLT is uncertain, it may be reasonable to measure CAC to reclassify those with minimal (1-10) or no CAC to avoid LLT. |
Adults With Chronic Kidney Disease—Stage 3 or Higher
The recommendations for patients with CKD are shown in table 11.
Table 11.
Recommendations for Patients with CKD
| In adults 40 to 75 years of age with CKD stage 3 or higher and an LDL-C of 70 to 189 mg/dL, moderate-intensity statin therapy or moderate-intensity statin combined with ezetimibe is recommended to reduce ASCVD risk |
| In adults with CKD stage 3 or higher and clinical ASCVD, LLT with high-intensity statin therapy, with or without ezetimibe and/or a PCSK9 mAb, is recommended to achieve a >50% reduction in LDL-C levels and a goal LDL-C <55 mg/dL and non–HDL-C <85 mg/dL |
| In adults with CKD who require maintenance hemodialysis, it may be reasonable to continue statin therapy to reduce the risk of ASCVD events. Treatment decisions should be individualized with consideration of expected survival, other comorbidities, and severity of ASCVD |
| In adults with CKD who require dialysis treatment, initiation of a statin has not been shown to be beneficial |
Persons Living With HIV
The recommendation for persons living with HIV is shown in table 12.
Table 12.
Recommendations for Persons Living With HIV
| In people living with HIV aged 40 to 75 years on stable combination antiretroviral therapy, statin therapy is recommended to reduce risk of a first ASCVD event and reduce the rate of coronary atherosclerosis progression |
Adults With Cancer or History of Cancer
The recommendations for adults with cancer or history of cancer are shown in table 13. Notably, in cancer survivors at low oncologic risk, the risk of heart disease death is greater than the risk of cancer death.
Table 13.
Recommendations for Adults with Cancer or History of Cancer
| Adult cancer survivors with life expectancy of at least 2 years who otherwise qualify for LLT should be treated similarly to people without a history of cancer to reduce the risk of ASCVD events |
| In adults with active cancer currently on statin therapy, treatment should be continued to reduce ASCVD risk unless there is concern for a specific drug interaction or life expectancy is <1 year |
| In adults with active cancer, initiation of statin therapy may be considered to prevent anthracycline-induced cardiotoxicity |
Management of Hypertriglyceridemia
The recommendations for the management of hypertriglyceridemia are shown in table 14 and figures 7-9.
Table 14.
Recommendations for the Management of Hypertriglyceridemia
| In adults with persistently elevated TG levels >150 mg/dL, after evaluation and management of secondary causes, lifestyle management is recommended as the first-line approach to reduce TG levels |
| In adults with clinical ASCVD and LDL-C >55 mg/dL and non–HDL-C >85 mg/dL on maximally tolerated statin with persistently elevated TG levels >150 to 999 mg/dL, intensification of LDL-C–lowering therapy is recommended to reduce ASCVD risk |
| In adults with familial chylomicronemia syndrome and fasting TG >1000 mg/dL, olezarsen is recommended as an adjunct to diet to lower TG levels and reduce the risk of pancreatitis |
| In adults >50 years of age with clinical ASCVD or with diabetes and 1 or more ASCVD risk factors, with persistently elevated TG levels 150 to 499 mg/dL and LDL-C <100 mg/dL on maximally tolerated statin, the addition of icosapent ethyl may be reasonable to lower ASCVD risk. |
| In adults aged 40 to 75 years without a history of ASCVD or diabetes who have persistently elevated TG levels 150 to 499 mg/dL, it is recommended to estimate 10-year ASCVD risk by the PREVENT-ASCVD equations to guide the benefit-risk discussion regarding further optimization of diet and lifestyle management as well as the potential initiation of statin therapy to reduce ASCVD risk |
| In adults with severe hypertriglyceridemia (persistently elevated TG levels 500-999 mg/dL and especially with TG levels >1000 mg/dL despite dietary intervention, the use of fibric acid derivatives or prescription omega-3 fatty acids is reasonable to lower TG levels and reduce the risk of pancreatitis |
| In adults with hypertriglyceridemia (TG >150 mg/dL), measurement of non–HDL-C or apoB is preferred over LDL-C to guide clinical decision making |

Figure 7.
Management of hypertriglyceridemia in patients with ASCVD.

Figure 8.
Management of hypertriglyceridemia in patients without ASCVD or Diabetes.

Figure 9.
Management of patients with triglycerides > 500mg/dL.
Approach to Patients with Elevated Lp(a)
The management of patients with elevated Lp(a) levels is shown in table 15.
Table 15.
Management of Patients with Elevated Lp(a) Levels
| In all individuals with elevated Lp(a) (>125 nmol/L or >50 mg/dL), optimal early control of modifiable cardiovascular risk factors is recommended to reduce ASCVD risk |
| In individuals with clinical ASCVD and elevated Lp(a) who have not achieved LDL-C and non–HDL-C treatment goals on maximally tolerated statin therapy, the addition of a PCSK9 mAb is recommended to achieve treatment goals and reduce ASCVD risk. PCSK9 mAb lower Lp(a) by 20-30% |
Summary of Goals of Therapy

Figure 10.
ACC/AHA Goals of therapy.
ESC/EAS GUIDELINES FOR THE MANAGEMENT OF DYSLIPIDEMIAS
Lipid Measurements
A standard serum lipid profile measures the concentration of total cholesterol, TG, and HDL-C.
LDL-C concentration can be estimated by the Friedewald equation and non-HDL-C can be calculated as total cholesterol minus HDL-C and is a measure of the total cholesterol carried by all atherogenic lipoproteins. A fasting or non-fasting standard lipid profile (total cholesterol, LDL-C, HDL-C, TG, and non-HDL-C is recommended. In most studies, non-fasting samples display a higher TG level of 0.3mmol/L (27mg/dL). On average, and for most individuals, this increment will be of no clinical significance. For general risk screening, non-fasting samples seem to have at least the same prognostic value as fasting samples. Apo B analysis is recommended for risk assessment, particularly in people with high TG levels, diabetes, obesity, metabolic syndrome, or very low LDL-C levels. It can be used as an alternative to LDL-C, if available, as the primary measurement for screening, diagnosis, and management, and may be preferred over non-HDL-C in people with high TG levels, DM, obesity, or very low LDL-C levels. Lp(a) measurement should be considered at least once in each adult person’s lifetime particularly in patients with a family history of premature CVD. Lp(a) measurement can be helpful for reclassification of patient risk in people who are borderline between risk categories.
Effects of Lifestyle Changes on Lipids
Lifestyle is the initial treatment in patients with dyslipidemia. The effect of lifestyle changes on lipid levels is shown in table 16. Recommended dietary choices to lower LDL-C are shown in table 17.
Table 16.
Effect of Lifestyle Changes on Lipid Levels
| Magnitude of Effect | |
|---|---|
| Lifestyle Interventions to reduce total cholesterol and LDL-C | |
| Avoid dietary trans fats Reduce dietary saturated fats Increase dietary fiber Use functional foods enriched with phytosterols Reduce excessive body weight Reduce dietary cholesterol Increase physical activity | ++ ++ ++ ++ + + + |
| Lifestyle interventions to reduce TG-rich lipoprotein levels | |
| Reduce excessive body weight Reduce alcohol intake Increase physical activity Reduce total amount of dietary carbohydrates Supplements of n-3 polyunsaturated fats Reduce intake of mono-and disaccharides Replace saturated fats with mono-or polyunsaturated fats | ++ +++ ++ ++ ++ ++ + |
| Lifestyle interventions to increase HDL-C levels | |
| Avoid dietary trans fats Increase physical activity Reduce excessive body weight Reduce dietary carbohydrates and replace with unsaturated fats Modest alcohol consumption may be continued Quit smoking | ++ +++ ++ ++ ++ + |
Table 17.
Food Choices to Decrease LDL-C and Improve Lipoprotein Profile
| To be preferred | To be used in moderation | To be chosen occasionally in limited amounts | |
|---|---|---|---|
| Cereals | Wholegrains | Refined bread, rice, and pasta, biscuits, corn flakes | Pastries, muffins, pies, croissants |
| Vegetables | Raw and cooked vegetables | Potatoes | Vegetables prepared in butter or cream |
| Legumes | Lentils, beans, fava beans, peas, chickpeas, soybean | ||
| Fruit | Fresh or frozen fruit | Dried fruit, jelly, jam, canned fruit, sorbets, ice lollies/popsicles, fruit juice | |
| Sweets and sweeteners | Non-caloric sweeteners | Sucrose, honey, chocolate, sweets/candies | Cakes, ice creams, fructose, soft drinks |
| Meat and fish | Lean and oily fish, poultry without skin | Lean cuts of beef, lamb, pork, and veal, seafood, shellfish | Sausages, salami, bacon, spareribs, hot dogs, organ meats |
| Dairy food and eggs | Skimmed milk and yoghurt | Low-fat milk, low-fat cheese and other milk products, eggs | Regular cheese, cream, whole milk and yoghurt |
| Cooking fat and dressings | Vinegar, mustard, fat-free dressings | Olive oil, non-tropical vegetable oils, soft margarines, salad dressing, mayonnaise, ketchup | Trans fats and hard margarines (better to avoid them), palm and coconut oils, butter, lard, bacon fat |
| Nuts/seeds | All, unsalted (except coconut) | Coconut | |
| Cooking procedures | Grilling, boiling, steaming | Stir-frying, roasting | Frying |
Estimation of Risk in Individuals Without ASCVD
In 2021 SCORE (Systematic Coronary Risk Estimation) was replaced by SCORE2, which updated the risk prediction algorithms and determines the risk of cardiovascular disease which includes cardiovascular mortality, non-fatal myocardial infarction, and ischemic stroke endpoints ((https://www.escardio.org/Education/ESC-Prevention-of-CVD-Programme/Risk-assessment/esc-cvd-risk-calculation-app). The ESC/EAS guidelines recommend the use of SCORE2, SCORE2-OP, and SCORE- Diabetes for estimating the risk of ASCVD over the next 10 years in persons without known CVD. SCORE2 estimates risk in individuals between 40-69 years of age. SCORE-OP estimates risk in individuals 70 years and older, and SCORE- Diabetes estimates risk in individuals with diabetes. The SCORE algorithms should not be used for individuals already taking lipid lowering drugs.
The variables used in SCORE2 to calculate risk are age (40-69), sex, smoking, systolic BP, total cholesterol, HDL-C (which allows for the calculation of non-HDL-C), and whether they live in a low, moderate, high, or very high-risk region (Table 18). SCORE2 provides an estimate of the 10-year risk of cardiovascular disease. SCORE2-OP uses the same variables as SCORE2. SCORE2 and SCORE-OP should not be used in individuals with diabetes, CKD, or genetic/rare lipid or BP disorders. In patients with diabetes the SCORE2- Diabetes, which uses the same variables as SCORE-2, but also includes HbA1c, age at diagnosis of diabetes, and eGFR should be used to estimate the 10-year risk of cardiovascular disease.
Table 18.
Country Classification for SCORE2
| Low Risk | Moderate Risk | High Risk | Very High Risk |
|---|---|---|---|
| Belgium Denmark France Israel Luxembourg Norway Spain Switzerland Netherlands United Kingdom | Austria Cyprus Finland Germany Greece Iceland Ireland Italy Malta, Portugal San Marino Slovenia Sweden | Albania Bosnia and Herzegovina Croatia Czech Republic Estonia Hungary Kazakhstan Poland Slovakia Turkey | Algeria Armenia Azerbaijan Belarus Bulgari Egypt Georgia Kyrgyzstan Latvia Lebanon Libya Lithuania Montenegro Morocco Republic of Moldova Romania Russian Federation Serbia Syria The Former Yugoslav Republic (Macedonia) Tunisia Ukraine Uzbekistan |
Clinical conditions and selected biomarkers are risk modifiers (table 19). Their presence may support reclassifying an individual to a higher risk category than would be calculated by the SCORE2 or SCORE2-OP algorithm. In addition, arterial (carotid and/or femoral) plaque burden should be considered as a risk modifier in individuals at low or moderate risk. Subclinical atherosclerosis by imaging or increased CAC score should be considered as risk modifiers in individuals at moderate risk or individuals close to treatment decision thresholds.
Table 19.
Risk Modifiers
| Demographic/clinical conditions • Family history of premature CVD (men: <55 years; women: <60 years) • High-risk ethnicity (e.g. Southern Asian) • Stress symptoms and psychosocial stressors • Social deprivation • Obesity • Physical inactivity • Chronic immune-mediated/inflammatory disorders • Major psychiatric disorders • History of premature menopause • Pre-eclampsia or other hypertensive disorders of pregnancy • Human immunodeficiency virus infection • Obstructive sleep apnea syndrome |
| Biomarkers • Persistently elevated hs-CRP (>2 mg/L) • Elevated Lp(a) >50 mg/dL (>105 nmol/L) |
Cardiovascular Risk Categories
Cardiovascular risk categories are shown in figure 11.

Figure 11.
Cardiovascular risk categories. ACS, acute coronary syndromes; CABG, coronary artery bypass graft surgery; PCI, percutaneous coronary intervention; a Typically defined by >50% stenosis. b e.g. CAC score >300. c Target organ damage is defined as microalbuminuria, retinopathy, or neuropathy.
Treatment Approach Based on Cardiovascular Risk and Untreated LDL-C Level
The treatment approach based on cardiovascular risk and untreated LDL-C level is shown in figure 12.

Figure 12.
Treatment approach based on cardiovascular risk and untreated LDL-C level.
Figure 13 shows the LDL-C treatment goals.

Figure 13.
LDL-C treatment goals.
The following secondary goals are recommended for non-HDL-C and Apo B.
- Very High Risk- non-HDL-C <2.2mmol/L (<85mg/dL); Apo B <65mg/dL
- High Risk- non-HDL-C <2.6mmol/L (<100mg/dL); Apo B <80mg/dL
- Moderate Risk- <3.4mmol/L (<130mg/dL; Apo B <100mg/dL
Medication Use
Figure 14 indicates the effectiveness of various LDL-C drugs as monotherapy and in combinations. Non-statin therapies with proven cardiovascular benefit (ezetimibe, PCSK9 monoclonal antibodies, and bempedoic acid) can be given in combination with statins to further lower LDL-C levels and reduce CV events. The choice should be based on the magnitude of additional LDL-C lowering needed.
In statin intolerant patients non-statin therapies with proven cardiovascular benefit (ezetimibe, PCSK9 monoclonal antibodies, and bempedoic acid) taken alone or in combination, are recommended to lower LDL-C levels and reduce the risk of CV events. The treatment choice should be based on the magnitude of LDL-C lowering needed.
A lipid profile should be obtained 4-12 weeks after initiation of therapy or after changes in therapy to ensure that LDL-C is at goal. Once at goal a lipid profile can be checked annually unless there are concerns regarding compliance.

Figure 14.
LDL-C lowering with drug therapy.
Primary Prevention
Table 20.
Recommendations for LDL-C Lowering Therapy in Primary Prevention Patients
| Pharmacological LDL-C-lowering therapy is recommended in patients: • at very high risk and LDL-C >1.8 mmol/L (70 mg/dL), or • at high risk and LDL-C >2.6 mmol/L (100 mg/dL) despite optimization of non-pharmacological measures, to lower CVD risk. |
| Pharmacological LDL-C-lowering therapy should be considered in patients: • at very high risk and LDL-C >1.4 mmol/L (55 mg/dL) but <1.8 mmol/L (70 mg/dL), or • at high risk and LDL-C ≥1.8 mmol/L (70 mg/dL) but <2.6 mmol/L (100 mg/dL), or • at moderate risk and LDL-C ≥2.6 mmol(L (100 mg/dL) but <4.9 mmol/L (190 mg/dL), or • at low risk and LDL-C ≥3.0 mmol/L (116 mg/dL) but <4.9 mmol/L (190 mg/dL) despite optimization of non-pharmacological measures, to lower CVD risk |
Recommendations for the Treatment of Dyslipidemia in Women
Table 21.
Recommendations for the Treatment of Dyslipidemia in Women
| Statin treatment is recommended for primary prevention of ASCVD in high-risk women |
| Statins are recommended for secondary prevention in women with the same indications and goals as in men |
| Lipid-lowering drugs should not be given when pregnancy is planned, during pregnancy, or during the breast-feeding period. However, for severe FH patients, bile acid sequestrants and/or LDL apheresis may be considered. |
Recommendations for the Treatment of Dyslipidemia in Older People (aged>65years)
Table 22.
Recommendations for the Treatment of Dyslipidemias in Older People (aged>65years)
| Treatment with statins is recommended for older people with ASCVD in the same way as for younger patients |
| Treatment with statins is recommended for primary prevention, according to the level of risk, in older people aged <75years |
| Initiation of statin treatment for primary prevention in older people aged >75 years may be considered, if at high-risk or greater risk |
| It is recommended that the statin is started at a low dose if there is significant renal impairment and/or the potential for drug interactions, and then titrated upwards to achieve LDL-C treatment goals |
Recommendations for the Treatment of Dyslipidemias in Patients with Diabetes Mellitus
Table 23.
Recommendations for the Treatment of Dyslipidemias in Patients with Diabetes Mellitus
| In patients with T2DM at very-high risk an LDL-C reduction of >50%from base line and an LDL-C goal <1.4mmol/L (<55mg/dL) is recommended. |
| In patients with T2DM at high risk an LDL-C reduction of >50% from baseline and an LDL-C goal <1.8mmol/L (<70mg/dL) is recommended |
| Statins are recommended in patients with T1DM who are at high or very-high risk. |
| Intensification of statin therapy should be considered before the introduction of combination therapy |
| If the goal is not reached, statin combination with ezetimibe should be considered |
| Statin therapy may be considered in both T1DM and T2DM patients aged <30years With evidence of end organ damage and/or an LDL-C level>2.5mmol/L (98mg/dL) |
Recommendations for the Treatment of Dyslipidemias in Patients with Chronic Kidney Disease
Table 24.
Recommendations for the Treatment of Dyslipidemias in Patients with Chronic Kidney Disease
| Patients with stage 3-5 CKD are considered to be at high or very-high risk of ASCVD |
| The use of statins or statin/ezetimibe combination is recommended in patients with non-dialysis-dependent stage 3-5 CKD |
| In patients already on statins, ezetimibe, or a statin/ezetimibe combination at the time of dialysis initiation, continuation of these drugs should be considered, particularly in patients with ASCVD |
| In patients with dialysis-dependent CKD who are free of ASCVD, commencement of statin therapy is not recommended |
Recommendations for the Treatment of Dyslipidemia in Patients Living with HIV
Table 25.
Recommendations for the Treatment of Dyslipidemia in Patients Living with HIV
| Statin therapy is recommended for people in primary prevention aged >40 years with HIV, irrespective of estimated cardiovascular risk and LDL-C levels, to reduce the risk of cardiovascular events; the choice of statin should be based on potential drug interactions. |
Recommendations for the Treatment of Dyslipidemia in Patients with a Prior Ischemic Stroke
Table 26.
Recommendations for the Treatment of Dyslipidemia in Patients with a Prior Ischemic Stroke
| Patients with a history of ischemic stroke or TIA are at very high-risk of ASCVD, particularly recurrent ischemic stroke , so it is recommended that they receive intensive LDL-C lowering therapy |
Recommendations for the Treatment of Dyslipidemias in Patients with Peripheral Arterial Disease
Table 27.
Recommendations for the Treatment of Dyslipidemias in Patients with Peripheral Arterial Disease
| In patients with PAD, lipid-lowering therapy, including a maximum tolerated dose of statin, plus ezetimibe or a combination with a PCSK9 inhibitor if needed, is recommended to reduce the risk of ASCVD events |
Recommendations for the Treatment of Dyslipidemias in Patients with Chronic Heart Failure or Valvular Heart Diseases
Table 28.
Recommendations for the Treatment of Dyslipidemias in Patients with Chronic Heart Failure or Valvular Heart Diseases
| Initiation of lipid-lowering therapy is not recommended in patients with HF in the absence of other indications for their use |
| Initiation of lipid-lowering treatment in patients with aortic valvular stenosis without CAD to slow progression of aortic valve stenosis in the absence of other indications for their use is not recommended |
Recommendations for the Treatment of Dyslipidemias in Patients with Heterozygous Familial Hypercholesterolemia
Table 29.
Recommendations for the Treatment of Dyslipidemias in Patients with Familial Hypercholesterolemia
| It is recommended that FH should be diagnosed using clinical criteria and confirmed, when possible, via DNA analysis |
| Once the index case is diagnosed, family cascade screening is recommended |
| It is recommended that FH patients with ASCVD or who have another major risk factor are treated as very-high-risk- a >50% reduction from baseline and an LDL-C <1.4 mmol/L (<55 mg/dL) |
| It is recommended that FH patients with no prior ASCVD or other risk factors are treated as high-risk - >50% reduction of LDL-C from baseline and an LDL-C 1.8mmol/L (<70mg/dL) |
| If goals cannot be achieved, a drug combination is recommended. Treatment with a PCSK9 inhibitor is recommended in very-high-risk FH patients if the treatment goal is not achieved on maximal tolerated statin plus ezetimibe |
Recommendations for the Treatment of Dyslipidemia in Patients with Acute Coronary Syndrome (ACS)
Table 30.
Recommendations for the Treatment of Dyslipidemia in Patients with ACS
| Intensification of LLT during the index ACS hospitalization is recommended for patients who were on any LLT before admission to further lower LDL-C levels |
| Initiating combination therapy with high-intensity statin plus ezetimibe during index hospitalization for ACS should be considered in patients who were treatment-naive and are not expected to achieve the LDL-C goal with statin therapy alone |
| LDL-C goal is < 1.4mmol/L (< 55mg/dL) |
| In patients with ASCVD who experience recurrent vascular events while taking maximally tolerated statin-based therapy or have polyvascular disease (e.g. coronary artery and peripheral artery disease) the LDL goal is < 1mmol/L (40mg/dL) |
Recommendations for the Treatment of Dyslipidemias in Patients with Solid Organ Transplants
Table 31.
Recommendations for the Treatment of Dyslipidemias in Patients with Solid Organ Transplants
| Statins should be considered as first-line agents in transplant patients. Initiation should be at low doses with careful up-titration and with caution regarding potential drug-drug interactions, particularly for patients on cyclosporin |
| In patients who are intolerant of statins or those with significant dyslipidemia despite maximally tolerated statin treatment, alternative or additional therapy with ezetimibe may be considered |
Recommendations for the Treatment of Dyslipidemia in Patients with Hypertriglyceridemia
Table 32.
Recommendations for the Treatment of Dyslipidemia in Patients with Hypertriglyceridemia
| High-dose icosapent ethyl (2 × 2 g/day) should be considered in combination with a statin in high-risk or very high-risk patients with elevated TG (fasting level 135–499 mg/dL or 1.52–5.63 mmol/L) to reduce the risk of cardiovascular events |
| Volanesorsen (300 mg/week) should be considered in patients with severe hypertriglyceridemia (>750 mg/dL or >8.5 mmol/L) due to familial chylomicronemia syndrome, to lower TG levels and reduce the risk of pancreatitis |
Recommendations for Patients with Cancer at High or Very High Chemotherapy-Related Cardiovascular Toxicity Risk
Table 33.
Recommendations for Patients with Cancer at High or Very High Chemotherapy-Related Cardiovascular Toxicity Risk
| Statins should be considered in adult patients at high or very high risk of developing chemotherapy-related cardiovascular toxicity to reduce the risk of anthracycline-induced cardiac dysfunction |
KEY PRINCIPLES
There are certain key principles that clinicians should utilize when deciding who to treat and how aggressively to treat hypercholesterolemia. Understanding these principles will allow clinicians to help their patients decide on the best approach to LDL-C lowering.
The Sooner the Better
It is widely recognized that atherosclerosis begins early in life and slowly progresses ultimately resulting in clinical manifestations later in life (8). Several studies have demonstrated the presence of atherosclerosis in young individuals (9-13). The extent of the atherosclerotic lesions correlates positively with total cholesterol and LDL-C and negatively with HDL-C levels (9,10,13-20). These studies clearly demonstrate that atherosclerosis begins early in life with the prevalence increasing with age and the extent and onset of lesions is influenced by total cholesterol and LDL-C levels. Moreover, an increased total cholesterol early in life also predicted an increased risk of developing cardiovascular disease later in life (21-23).
Genetic studies have further illustrated the key role of exposure to total cholesterol and LDL-C in determining the time when clinical manifestations of ASCVD occur. In patients with homozygous familial hypercholesterolemia (FH), LDL-C are markedly elevated, and cardiovascular events can occur early in life. Greater than 50% of untreated patients with homozygous FH develop clinically significant ASCVD by the age of 30 and cardiovascular events can occur before age 10 in some patients (24). In patients with heterozygous FH LDL-C levels are elevated but not to the levels seen with homozygous FH and cardiovascular events occur later in life but still at a relatively younger age. Untreated males with heterozygous FH have a 50% risk for a fatal or non-fatal myocardial infarction by 50 years of age whereas untreated females have a 30% chance by age 60 (24). Conversely, individuals with genetic variants in PCSK9, HMG-CoA reductase, LDL receptor, NPC1L1, or ATP citrate lyase that lead to a decrease in LDL-C levels have a reduced risk of developing cardiovascular events (25,26). The relationship between genetic disorders that alter LDL-C levels and the time to develop clinical cardiovascular events is illustrated in figure 15. The figure clearly illustrates that the age when one clinically manifests ASCVD depends on the level of LDL-C. With very high LDL-C levels clinical events occur early in life and with low LDL-C levels events will occur at an older age leading to the concept of LDL years (i.e., level of LDL-C and the number of years exposed).

Figure 15.
Relationship between cumulative LDL-C exposure, age, and the development of the clinical manifestations of ASCVD. Figure from reference (26).
Of major importance is that the reduction in ASCVD events is much greater in individuals with lifelong decreases in LDL-C compared to the reductions in ASCVD events seen with statin treatment (Table 34). A lifelong 10mg/dL decrease in LDL-C due to polymorphisms in genes that affect LDL-C is associated with a 16-18% decrease in ASCVD events (25). In contrast, a decrease in LDL-C of 39mg/dL over 4-5 years with statin therapy results in only a 22% decrease in ASCVD events (27,28). Thus, a life-long decrease in LDL-C levels results in a decrease in cardiovascular events that is three to four times as great as that seen with short-term LDL-C lowering with drugs. Figure 16 illustrates the benefits of early treatment in reducing LDL-C years and delaying the development of ASCVD.
Table 34.
Effect of Reduction in LDL-C by Genetic Variants on the Risk of ASCVD
| Gene | Odds ratio for ASCVD events per 10mg/dL decrease in LDL-C (95% CI) |
|---|---|
| ATP citrate lyase | 0.82 (0.78–0.87) |
| HMG CoA reductase | 0.84 (0.82–0.87) |
| NPC1L1 | 0.84 (0.79–0.89) |
| PCSK9 | 0.83 (0.80–0.87) |
| LDL receptor | 0.83 (0.80–0.87) |
Statin treatment decreases ASCVD by approximately 20% per 39mg/dL decrease in LDL-C (27).

Figure 16.
The effect of early lowering of LDL-C on the development of ASCVD.
In addition to calculating the 10-year risk of ASCVD events it is important to calculate either the lifetime or 30-year risk. This is particularly important in younger individuals where the 10-year risk of ASCVD events may be relatively low, but the long-term risk may be high. In the discussion of therapy with patients, they need to be aware of their long-term risk and the potential advantages of early treatment.
Lowering LDL-C levels by lifestyle changes early in life will have long-term benefits. Additionally, in selected individuals initiating drug therapy sooner rather than latter will reduce ASCVD events later in life.
The Lower the Better
A variety of different types of studies have clearly demonstrated that greater reductions of LDL-C results in a more robust decrease in ASCVD events.
- 1.
Statin trials have demonstrated that ASCVD events are decreased even in patients with low LDL-C levels (29). In patients with an LDL-C less than 70mg/dL, statin treatment still resulted in a 37% decrease in ASCVD events despite the patients having a low baseline LDL-C.
- 2.
Intensive statin therapy results in a greater decrease in LDL-C levels compared to moderate statin therapy. Moreover, intensive therapy also results in a greater decrease in ASCVD events (29).
- 3.
Adding ezetimibe to statin therapy resulted in a lower LDL-C than statin therapy alone and furthermore decreased ASCVD events (30).
- 4.
Adding a PCSK9 inhibitor to statin therapy decreases LDL-C levels and results in a greater reduction in ASCVD events than statins alone (31,32).
- 5.
Randomized trials have shown that a lower LDL-C goal results in a decrease in ASCVD events (33,34).
Taken together these studies clearly demonstrate that the lower the LDL-C level the greater the decrease in ASCVD events. However, there may be a threshold where further lowering of LDL-C does not result in further benefits. In the ODYSSEY trial using the PCSK9 inhibitor alirocumab, the decrease in ASCVD events was similar in patients with an LDL-C less than 25mg/dL and those with an LDL-C between 25-50mg/dL (35). Future studies are required to define if there is a threshold where further LDL-C lowering is no longer beneficial.
Clinicians need to balance the benefits of more aggressively lowering LDL-C levels with the risks and costs of high dose or additional drug therapy. Both statins and ezetimibe are generic drugs and very inexpensive. Thus, in many patients the use of the combination of a statin (either high intensity or moderate intensity) and ezetimibe will maximize the decrease in LDL-C and more effectively reduce ASCVD events, with minimal risk and at low cost. In contrast, PCSK9 inhibitors and bempedoic acid are relatively expensive, and clinicians will need to balance the benefits and the increased costs.
The Higher the LDL-C the Greater the Benefit
The percent decrease in LDL-C levels that occurs with statin treatment or the use of other LDL-C lowering drugs is similar regardless of the baseline LDL-C level (36). However, the absolute decrease in LDL-C will be greater if the starting LDL-C is higher. The Cholesterol Treatment Trialists demonstrated that the relative risk reduction in cardiovascular events per 39mg/dL (1mmol/L) decrease in LDL-C is similar in patients with a low or high baseline LDL-C level. Thus, as shown in table 35 the treatment of patients with high baseline LDL-C levels will result in greater decreases in ASCVD events. A meta-analysis of 34 trials with 270,288 individuals found that LDL-C lowering was associated with a progressively greater relative risk reduction in ASCVD events in patients with increased baseline LDL-C levels (37).
Table 35.
The Higher the Baseline LDL-C the Greater the Reduction in ASCVD
| Baseline LDL-C 80mg/dL | Baseline LDL-C 160mg/dL |
|---|---|
| Atorvastatin 80mg reduces LDL-C by 50% to 40mg/dl (40mg/dL decrease) | Atorvastatin 80mg reduces LDL-C by 50% to 80mg/dl (80mg/dL decrease) |
| A 40mg/dL decrease in LDL-C will result in an approximate 22% decrease in ASCVD events | An 80mg/dL decrease in LDL-C will result in an approximate 44% decrease in ASCVD events |
The Greater the Risk of ASCVD the Greater the Benefit
Analysis by the Cholesterol Treatment Trialists found that the relative risk reduction was similar regardless of the underlying ASCVD risk (27). However, the absolute risk reduction was much greater in patients with a high risk of ASCVD (table 36) (27). Additionally, studies have shown that in patients with a high polygenic risk score for ASCVD events statin therapy reduces ASCVD events to a greater extent again indicating the higher the risk the greater the benefit of lowering LDL-C (38,39).
Table 36.
Risk of Cardiovascular Events in High and Low Risk Patients
| 5-year event risk | Relative Risk (CI) per 39mg/dL reduction in LDL-C | Absolute Decrease in Events per Annum* |
|---|---|---|
| <10% | 0.68 (0.62-0.74) | 0.3% |
| 10-20% | 0.79 (0.75-0.84) | 0.5% |
| 20-30% | 0.81 (0.78-0.85 | 1.1% |
| >30% | 0.79 (0.75-0.83 | 2.2% |
- *
Percent of patients on placebo having an event minus percent of patients on statin therapy having an event. Data from Cholesterol Treatment Trialists (27).
In the IMPROVE-IT trial lowering LDL-C with ezetimibe and the ODYSSEY and FOURIER trials using PCSK9 inhibitors a greater reduction in ASCVD events was observed in high risk patients (see reference (40) for discussion of these studies). Table 37 provides a list of indicators of high risk.
Table 37.
High Risk Indicators for ASCVD Events
| Diabetes Atherosclerosis in multiple sites (peripheral arterial disease, cerebral vascular disease, coronary arteries) History of prior coronary artery bypass graft surgery Acute coronary syndrome Multiple MIs Recent ASCVD events Genetic lipid disorders High polygenic risk score |
Summary
Following these general principles will help clinicians make informed decisions in deciding on their approach to lowering LDL-C levels and will facilitate discussions with patients on the benefits and risks of treatment. For an in-depth discussion of these key principles see the following references (40,41).
CONCLUSION
Advances in the drug therapy of dyslipidemia offer great potential for reducing both new-onset ASCVD and recurrent ASCVD events in those with established disease. This benefit can be enhanced by judicious use of lifestyle intervention (for additional information on diet see the Endotext chapter entitled “The Effect of Diet on Cardiovascular Disease and Lipid and Lipoprotein Levels” (42)). But among drugs, statins are first-line therapy. They are generally safe and inexpensive. They have been shown to reduce ASCVD events in both secondary and primary prevention. Ezetimibe has about half the LDL-lowering efficacy of statins; it too is generally safe and is a relatively inexpensive genetic drug. Ezetimibe can be used as an add-on drug to moderate intensity statins, especially for those who do not tolerate a high-intensity statin or in combination with high intensity statins to markedly decrease LDL-C levels. PCSK9 inhibitors are powerful LDL-lowering drugs, and they have a strong safety profile. The major drawback is cost. If the cost of these inhibitors can be reduced, they too have the potential for wide usage, especially in patients who are “statin intolerant”. Bempedoic acid has been shown to reduce ASCVD events in statin intolerant patients and in combination with ezetimibe can result in significant decreases in LDL-C levels. For additional information on cholesterol and triglyceride lowering drugs see the Endotext chapters that address these topics (36,43). A major challenge for use of cholesterol-lowering drugs is the problem of long-term non-adherence.
ACKNOWLEDGEMENTS
This chapter is dedicated to Dr. Grundy who has been an inspiration to lipidologists worldwide and has played a major role in establishing guidelines for the treatment of dyslipidemia to reduce ASCVD. He was the author of earlier versions of this chapter.
This work was supported by grants from the Northern California Institute for Research and Education.
REFERENCES
- 1.
- Aragam KG, Natarajan P. Polygenic Scores to Assess Atherosclerotic Cardiovascular Disease Risk: Clinical Perspectives and Basic Implications. Circ Res 2020; 126:1159-1177 [PMC free article: PMC7926201] [PubMed: 32324503]
- 2.
- Writing Committee Members, Blumenthal RS, Morris PB, Gaudino M, Johnson HM, Anderson TS, Bittner VA, Blankstein R, Brewer LC, Cho L, de Ferranti SD, Gianos E, Gluckman TJ, Gradney KF, Isiadinso I, Lloyd-Jones DM, Marrs JC, Martin SS, McLain KH, Mehta LS, Mora S, Mulugeta WM, Natarajan P, Navar AM, Orringer CE, Polonsky TS, Reynolds HR, Saseen JJ, Shapiro MD, Soffer DE, Tynes SA, Villavaso CD, Virani SS, Wilkins JT, Peer Review Committee M. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation 2026;
- 3.
- Blumenthal RS, Morris PB, Gaudino M, Johnson HM, Anderson TS, Bittner VA, Blankstein R, Brewer LC, Cho L, de Ferranti SD, Gianos E, Gluckman TJ, Gradney KF, Isiadinso I, Lloyd-Jones DM, Marrs JC, Martin SS, McLain KH, Mehta LS, Mora S, Mulugeta WM, Natarajan P, Navar AM, Orringer CE, Polonsky TS, Reynolds HR, Saseen JJ, Shapiro MD, Soffer DE, Tynes SA, Villavaso CD, Virani SS, Wilkins JT. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. J Am Coll Cardiol 2026; [PubMed: 41824590]
- 4.
- Mach F, Koskinas KC, Roeters van Lennep JE, Tokgozoglu L, Badimon L, Baigent C, Benn M, Binder CJ, Catapano AL, De Backer GG, Delgado V, Fabin N, Ference BA, Graham IM, Landmesser U, Laufs U, Mihaylova B, Nordestgaard BG, Richter DJ, Sabatine MS. 2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias. Eur Heart J 2025; 46:4359-4378
- 5.
- Mach F, Baigent C, Catapano AL, Koskinas KC, Casula M, Badimon L, Chapman MJ, De Backer GG, Delgado V, Ference BA, Graham IM, Halliday A, Landmesser U, Mihaylova B, Pedersen TR, Riccardi G, Richter DJ, Sabatine MS, Taskinen MR, Tokgozoglu L, Wiklund O. 2019 ESC/EAS Guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular risk. Eur Heart J 2020; 41:111-188 [PubMed: 31504418]
- 6.
- Daniels SR. Guidelines for Screening, Prevention, Diagnosis and Treatment of Dyslipidemia in Children and Adolescents. In: Feingold KR, Adler RA, Ahmed SF, Anawalt B, Blackman MR, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hamilton E, Hofland J, Jan de Beur S, Kalra S, Kaltsas G, Kapoor N, Kim M, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrere B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Rey R, Sahay R, Shah AS, Sperling MA, Stratakis CA, Trence DL, Wilson DP, eds. Endotext. South Dartmouth (MA)2020.
- 7.
- Wild R, Feingold KR. Effect of Pregnancy on Lipid Metabolism and Lipoprotein Levels. In: Feingold KR, Adler RA, Ahmed SF, Anawalt B, Blackman MR, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hamilton E, Hofland J, Jan de Beur S, Kalra S, Kaltsas G, Kapoor N, Kim M, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrere B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Rey R, Sahay R, Shah AS, Sperling MA, Stratakis CA, Trence DL, Wilson DP, eds. Endotext. South Dartmouth (MA)2026.
- 8.
- Wilson DP. Is Atherosclerosis a Pediatric Disease? In: Feingold KR, Anawalt B, Blackman MR, Boyce A, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hofland J, Kalra S, Kaltsas G, Kapoor N, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrere B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Sahay R, Shah AS, Singer F, Sperling MA, Stratakis CA, Trence DL, Wilson DP, eds. Endotext. South Dartmouth (MA)2025.
- 9.
- Berenson GS, Srinivasan SR, Bao W, Newman WP, 3rd, Tracy RE, Wattigney WA. Association between multiple cardiovascular risk factors and atherosclerosis in children and young adults. The Bogalusa Heart Study. N Engl J Med 1998; 338:1650-1656 [PubMed: 9614255]
- 10.
- McGill HC, Jr., McMahan CA, Malcom GT, Oalmann MC, Strong JP. Effects of serum lipoproteins and smoking on atherosclerosis in young men and women. The PDAY Research Group. Pathobiological Determinants of Atherosclerosis in Youth. Arterioscler Thromb Vasc Biol 1997; 17:95-106 [PubMed: 9012643]
- 11.
- Tuzcu EM, Kapadia SR, Tutar E, Ziada KM, Hobbs RE, McCarthy PM, Young JB, Nissen SE. High prevalence of coronary atherosclerosis in asymptomatic teenagers and young adults: evidence from intravascular ultrasound. Circulation 2001; 103:2705-2710 [PubMed: 11390341]
- 12.
- McNamara JJ, Molot MA, Stremple JF, Cutting RT. Coronary artery disease in combat casualties in Vietnam. JAMA 1971; 216:1185-1187 [PubMed: 5108403]
- 13.
- Webber BJ, Seguin PG, Burnett DG, Clark LL, Otto JL. Prevalence of and risk factors for autopsy-determined atherosclerosis among US service members, 2001-2011. JAMA 2012; 308:2577-2583 [PubMed: 23268516]
- 14.
- Newman WP, 3rd, Freedman DS, Voors AW, Gard PD, Srinivasan SR, Cresanta JL, Williamson GD, Webber LS, Berenson GS. Relation of serum lipoprotein levels and systolic blood pressure to early atherosclerosis. The Bogalusa Heart Study. N Engl J Med 1986; 314:138-144 [PubMed: 3455748]
- 15.
- McGill HC, Jr., McMahan CA. Determinants of atherosclerosis in the young. Pathobiological Determinants of Atherosclerosis in Youth (PDAY) Research Group. Am J Cardiol 1998; 82:30T-36T [PubMed: 9860371]
- 16.
- Davis PH, Dawson JD, Riley WA, Lauer RM. Carotid intimal-medial thickness is related to cardiovascular risk factors measured from childhood through middle age: The Muscatine Study. Circulation 2001; 104:2815-2819 [PubMed: 11733400]
- 17.
- Juonala M, Magnussen CG, Venn A, Dwyer T, Burns TL, Davis PH, Chen W, Srinivasan SR, Daniels SR, Kahonen M, Laitinen T, Taittonen L, Berenson GS, Viikari JS, Raitakari OT. Influence of age on associations between childhood risk factors and carotid intima-media thickness in adulthood: the Cardiovascular Risk in Young Finns Study, the Childhood Determinants of Adult Health Study, the Bogalusa Heart Study, and the Muscatine Study for the International Childhood Cardiovascular Cohort (i3C) Consortium. Circulation 2010; 122:2514-2520 [PubMed: 21126976]
- 18.
- Li S, Chen W, Srinivasan SR, Bond MG, Tang R, Urbina EM, Berenson GS. Childhood cardiovascular risk factors and carotid vascular changes in adulthood: the Bogalusa Heart Study. JAMA 2003; 290:2271-2276 [PubMed: 14600185]
- 19.
- Magnussen CG, Venn A, Thomson R, Juonala M, Srinivasan SR, Viikari JS, Berenson GS, Dwyer T, Raitakari OT. The association of pediatric low- and high-density lipoprotein cholesterol dyslipidemia classifications and change in dyslipidemia status with carotid intima-media thickness in adulthood evidence from the cardiovascular risk in Young Finns study, the Bogalusa Heart study, and the CDAH (Childhood Determinants of Adult Health) study. J Am Coll Cardiol 2009; 53:860-869 [PMC free article: PMC2759186] [PubMed: 19264243]
- 20.
- Raitakari OT, Juonala M, Kahonen M, Taittonen L, Laitinen T, Maki-Torkko N, Jarvisalo MJ, Uhari M, Jokinen E, Ronnemaa T, Akerblom HK, Viikari JS. Cardiovascular risk factors in childhood and carotid artery intima-media thickness in adulthood: the Cardiovascular Risk in Young Finns Study. JAMA 2003; 290:2277-2283 [PubMed: 14600186]
- 21.
- Klag MJ, Ford DE, Mead LA, He J, Whelton PK, Liang KY, Levine DM. Serum cholesterol in young men and subsequent cardiovascular disease. N Engl J Med 1993; 328:313-318 [PubMed: 8419817]
- 22.
- Pletcher MJ, Vittinghoff E, Thanataveerat A, Bibbins-Domingo K, Moran AE. Young Adult Exposure to Cardiovascular Risk Factors and Risk of Events Later in Life: The Framingham Offspring Study. PLoS One 2016; 11:e0154288 [PMC free article: PMC4854462] [PubMed: 27138014]
- 23.
- Stamler J, Daviglus ML, Garside DB, Dyer AR, Greenland P, Neaton JD. Relationship of baseline serum cholesterol levels in 3 large cohorts of younger men to long-term coronary, cardiovascular, and all-cause mortality and to longevity. JAMA 2000; 284:311-318 [PubMed: 10891962]
- 24.
- Warden BA, Fazio S, Shapiro MD. Familial Hypercholesterolemia: Genes and Beyond. In: Feingold KR, Anawalt B, Blackman MR, Boyce A, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hofland J, Kalra S, Kaltsas G, Kapoor N, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrère B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Sahay R, Shah AS, Singer F, Sperling MA, Stratakis CA, Trence DL, DP W, eds. Endotext. South Dartmouth (MA)2024.
- 25.
- Ference BA, Ray KK, Catapano AL, Ference TB, Burgess S, Neff DR, Oliver-Williams C, Wood AM, Butterworth AS, Di Angelantonio E, Danesh J, Kastelein JJP, Nicholls SJ. Mendelian Randomization Study of ACLY and Cardiovascular Disease. N Engl J Med 2019; 380:1033-1042 [PMC free article: PMC7612927] [PubMed: 30865797]
- 26.
- Horton JD, Cohen JC, Hobbs HH. PCSK9: a convertase that coordinates LDL catabolism. J Lipid Res 2009; 50 Suppl:S172-177 [PMC free article: PMC2674748] [PubMed: 19020338]
- 27.
- Cholesterol Treatment Trialists Collaborators, Fulcher J, O’Connell R, Voysey M, Emberson J, Blackwell L, Mihaylova B, Simes J, Collins R, Kirby A, Colhoun H, Braunwald E, La Rosa J, Pedersen TR, Tonkin A, Davis B, Sleight P, Franzosi MG, Baigent C, Keech A. Efficacy and safety of LDL-lowering therapy among men and women: meta-analysis of individual data from 174,000 participants in 27 randomised trials. Lancet 2015; 385:1397-1405 [PubMed: 25579834]
- 28.
- Cholesterol Treatment Trialists Collaborators, Mihaylova B, Emberson J, Blackwell L, Keech A, Simes J, Barnes EH, Voysey M, Gray A, Collins R, Baigent C. The effects of lowering LDL cholesterol with statin therapy in people at low risk of vascular disease: meta-analysis of individual data from 27 randomised trials. Lancet 2012; 380:581-590 [PMC free article: PMC3437972] [PubMed: 22607822]
- 29.
- Cholesterol Treatment Trialists’ Collaborators, Baigent C, Blackwell L, Emberson J, Holland LE, Reith C, Bhala N, Peto R, Barnes EH, Keech A, Simes J, Collins R. Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials. Lancet 2010; 376:1670-1681 [PMC free article: PMC2988224] [PubMed: 21067804]
- 30.
- Cannon CP, Blazing MA, Giugliano RP, McCagg A, White JA, Theroux P, Darius H, Lewis BS, Ophuis TO, Jukema JW, De Ferrari GM, Ruzyllo W, De Lucca P, Im K, Bohula EA, Reist C, Wiviott SD, Tershakovec AM, Musliner TA, Braunwald E, Califf RM. Ezetimibe Added to Statin Therapy after Acute Coronary Syndromes. New England Journal of Medicine 2015; 372:2387-2397 [PubMed: 26039521]
- 31.
- Sabatine MS, Giugliano RP, Keech AC, Honarpour N, Wiviott SD, Murphy SA, Kuder JF, Wang H, Liu T, Wasserman SM, Sever PS, Pedersen TR. Evolocumab and Clinical Outcomes in Patients with Cardiovascular Disease. New England Journal of Medicine 2017; 376:1713-1722 [PubMed: 28304224]
- 32.
- Schwartz GG, Steg PG, Szarek M, Bhatt DL, Bittner VA, Diaz R, Edelberg JM, Goodman SG, Hanotin C, Harrington RA, Jukema JW, Lecorps G, Mahaffey KW, Moryusef A, Pordy R, Quintero K, Roe MT, Sasiela WJ, Tamby J-F, Tricoci P, White HD, Zeiher AM. Alirocumab and Cardiovascular Outcomes after Acute Coronary Syndrome. New England Journal of Medicine 2018; 379:2097-2107 [PubMed: 30403574]
- 33.
- Lee YJ, Lee SJ, Kim JW, Lee SH, Kim GS, Park JH, Cho JM, Kang WC, Yoon HJ, Kim WH, Lee SJ, Lee JB, Jang JY, Shin S, Park IH, Kwon SU, Kim S, Hong SJ, Ahn CM, Kim JS, Ko YG, Choi D, Hong MK, Jang Y, Kim BK. Intensive LDL Cholesterol Targeting in Atherosclerotic Cardiovascular Disease. N Engl J Med 2026; 394:1365-1375 [PubMed: 41910315]
- 34.
- Amarenco P, Kim JS, Labreuche J, Charles H, Abtan J, Bejot Y, Cabrejo L, Cha JK, Ducrocq G, Giroud M, Guidoux C, Hobeanu C, Kim YJ, Lapergue B, Lavallee PC, Lee BC, Lee KB, Leys D, Mahagne MH, Meseguer E, Nighoghossian N, Pico F, Samson Y, Sibon I, Steg PG, Sung SM, Touboul PJ, Touze E, Varenne O, Vicaut E, Yelles N, Bruckert E, Treat Stroke to Target I. A Comparison of Two LDL Cholesterol Targets after Ischemic Stroke. N Engl J Med 2020; 382:9 [PubMed: 31738483]
- 35.
- Schwartz GG, Gabriel Steg P, Bhatt DL, Bittner VA, Diaz R, Goodman SG, Jukema JW, Kim YU, Li QH, Manvelian G, Pordy R, Sourdille T, White HD, Szarek M. Clinical Efficacy and Safety of Alirocumab After Acute Coronary Syndrome According to Achieved Level of Low-Density Lipoprotein Cholesterol: A Propensity Score-Matched Analysis of the ODYSSEY OUTCOMES Trial. Circulation 2021; 143:1109-1122 [PMC free article: PMC7969166] [PubMed: 33438437]
- 36.
- Feingold KR. Cholesterol Lowering Drugs. In: Feingold KR, Anawalt B, Blackman MR, Boyce A, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hofland J, Kalra S, Kaltsas G, Kapoor N, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrère B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Sahay R, Shah AS, Singer F, Sperling MA, Stratakis CA, Trence DL, DP W, eds. Endotext. South Dartmouth (MA)2024.
- 37.
- Navarese EP, Robinson JG, Kowalewski M, Kolodziejczak M, Andreotti F, Bliden K, Tantry U, Kubica J, Raggi P, Gurbel PA. Association Between Baseline LDL-C Level and Total and Cardiovascular Mortality After LDL-C Lowering: A Systematic Review and Meta-analysis. JAMA 2018; 319:1566-1579 [PMC free article: PMC5933331] [PubMed: 29677301]
- 38.
- Mega JL, Stitziel NO, Smith JG, Chasman DI, Caulfield M, Devlin JJ, Nordio F, Hyde C, Cannon CP, Sacks F, Poulter N, Sever P, Ridker PM, Braunwald E, Melander O, Kathiresan S, Sabatine MS. Genetic risk, coronary heart disease events, and the clinical benefit of statin therapy: an analysis of primary and secondary prevention trials. Lancet 2015; 385:2264-2271 [PMC free article: PMC4608367] [PubMed: 25748612]
- 39.
- Natarajan P, Young R, Stitziel NO, Padmanabhan S, Baber U, Mehran R, Sartori S, Fuster V, Reilly DF, Butterworth A, Rader DJ, Ford I, Sattar N, Kathiresan S. Polygenic Risk Score Identifies Subgroup With Higher Burden of Atherosclerosis and Greater Relative Benefit From Statin Therapy in the Primary Prevention Setting. Circulation 2017; 135:2091-2101 [PMC free article: PMC5484076] [PubMed: 28223407]
- 40.
- Feingold KR, Chait A. Approach to patients with elevated low-density lipoprotein cholesterol levels. Best Pract Res Clin Endocrinol Metab 2022:101658 [PubMed: 35487874]
- 41.
- Feingold KR. Maximizing the benefits of cholesterol-lowering drugs. Curr Opin Lipidol 2019; 30:388-394 [PubMed: 31335331]
- 42.
- Feingold KR. The Effect of Diet on Cardiovascular Disease and Lipid and Lipoprotein Levels. In: Feingold KR, Anawalt B, Blackman MR, Boyce A, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hofland J, Kalra S, Kaltsas G, Kapoor N, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrère B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Sahay R, Shah AS, Singer F, Sperling MA, Stratakis CA, Trence DL, DP W, eds. Endotext. South Dartmouth (MA)2024.
- 43.
- Feingold KR. Triglyceride Lowering Drugs. In: Feingold KR, Anawalt B, Blackman MR, Boyce A, Chrousos G, Corpas E, de Herder WW, Dhatariya K, Dungan K, Hofland J, Kalra S, Kaltsas G, Kapoor N, Koch C, Kopp P, Korbonits M, Kovacs CS, Kuohung W, Laferrère B, Levy M, McGee EA, McLachlan R, Muzumdar R, Purnell J, Sahay R, Shah AS, Singer F, Sperling MA, Stratakis CA, Trence DL, DP W, eds. Endotext. South Dartmouth (MA)2025.
- How effective are the ESC/EAS and 2013 ACC/AHA guidelines in treating dyslipidemia? Lessons from a lipid clinic.[Curr Med Res Opin. 2015]How effective are the ESC/EAS and 2013 ACC/AHA guidelines in treating dyslipidemia? Lessons from a lipid clinic.Barkas F, Milionis H, Kostapanos MS, Mikhailidis DP, Elisaf M, Liberopoulos E. Curr Med Res Opin. 2015 Feb; 31(2):221-8. Epub 2014 Nov 24.
- Review Clinical Management of Dyslipidemia in Youth with Chronic Kidney Disease.[Endotext. 2000]Review Clinical Management of Dyslipidemia in Youth with Chronic Kidney Disease.De La Torre A, Patni N, Wilson DP. Endotext. 2000
- Review New Recommendations and Revised Concepts in Recent Guidelines on the Management of Dyslipidemias to Prevent Cardiovascular Disease: the 2018 ACC/AHA and 2019 ESC/EAS Guidelines.[Curr Cardiol Rep. 2020]Review New Recommendations and Revised Concepts in Recent Guidelines on the Management of Dyslipidemias to Prevent Cardiovascular Disease: the 2018 ACC/AHA and 2019 ESC/EAS Guidelines.Raygor V, Khera A. Curr Cardiol Rep. 2020 Jul 9; 22(9):87. Epub 2020 Jul 9.
- Review Utility of Advanced Lipoprotein Testing in Clinical Practice.[Endotext. 2000]Review Utility of Advanced Lipoprotein Testing in Clinical Practice.Feingold KR. Endotext. 2000
- Review Transatlantic guidelines on dyslipidemia and cardiovascular risk: key differences across the pond.[Curr Opin Endocrinol Diabetes ...]Review Transatlantic guidelines on dyslipidemia and cardiovascular risk: key differences across the pond.Agha AM, Virani SS, Ballantyne CM. Curr Opin Endocrinol Diabetes Obes. 2021 Apr 1; 28(2):114-121.
- Guidelines for the Management of Dyslipidemia - EndotextGuidelines for the Management of Dyslipidemia - Endotext
Your browsing activity is empty.
Activity recording is turned off.
See more...